
A look at decade-long rotator cuff repair outcomes with MSC augmentation, tendon-to-bone healing, and the importance of cell quality.
Most patients hear "partial-thickness tear" and assume it's the mild version of the injury. The 10-year data on rotator cuff repair says otherwise: without biological augmentation, more than half of repairs fail structurally within a decade. The suture holds. The tendon rarely grows back into the bone completely or durably.
That gap between a technically successful surgery and a repair that holds is where mesenchymal stem cell (MSC) therapy has produced some of the clearest long-term data in medicine.
What a "Successful" Repair Looks Like at Year 10
A study published in International Orthopaedics followed patients for a full decade after arthroscopic rotator cuff repair, comparing outcomes with and without MSC augmentation at the time of surgery. MSC-augmented repairs were 100% healed at 6 months, compared to 67% in the control group. At the 10-year mark, 87% of the augmented repairs remained structurally intact, compared to 44% of the controls.
International Orthopaedics, 2014 — 10-year follow-up — MSC augmentation during arthroscopic repair nearly doubled long-term structural integrity.
Read that gap again. Nearly double the durability, a decade out, from cells added at the time of one surgery.
Where Standard Repair Falls Short
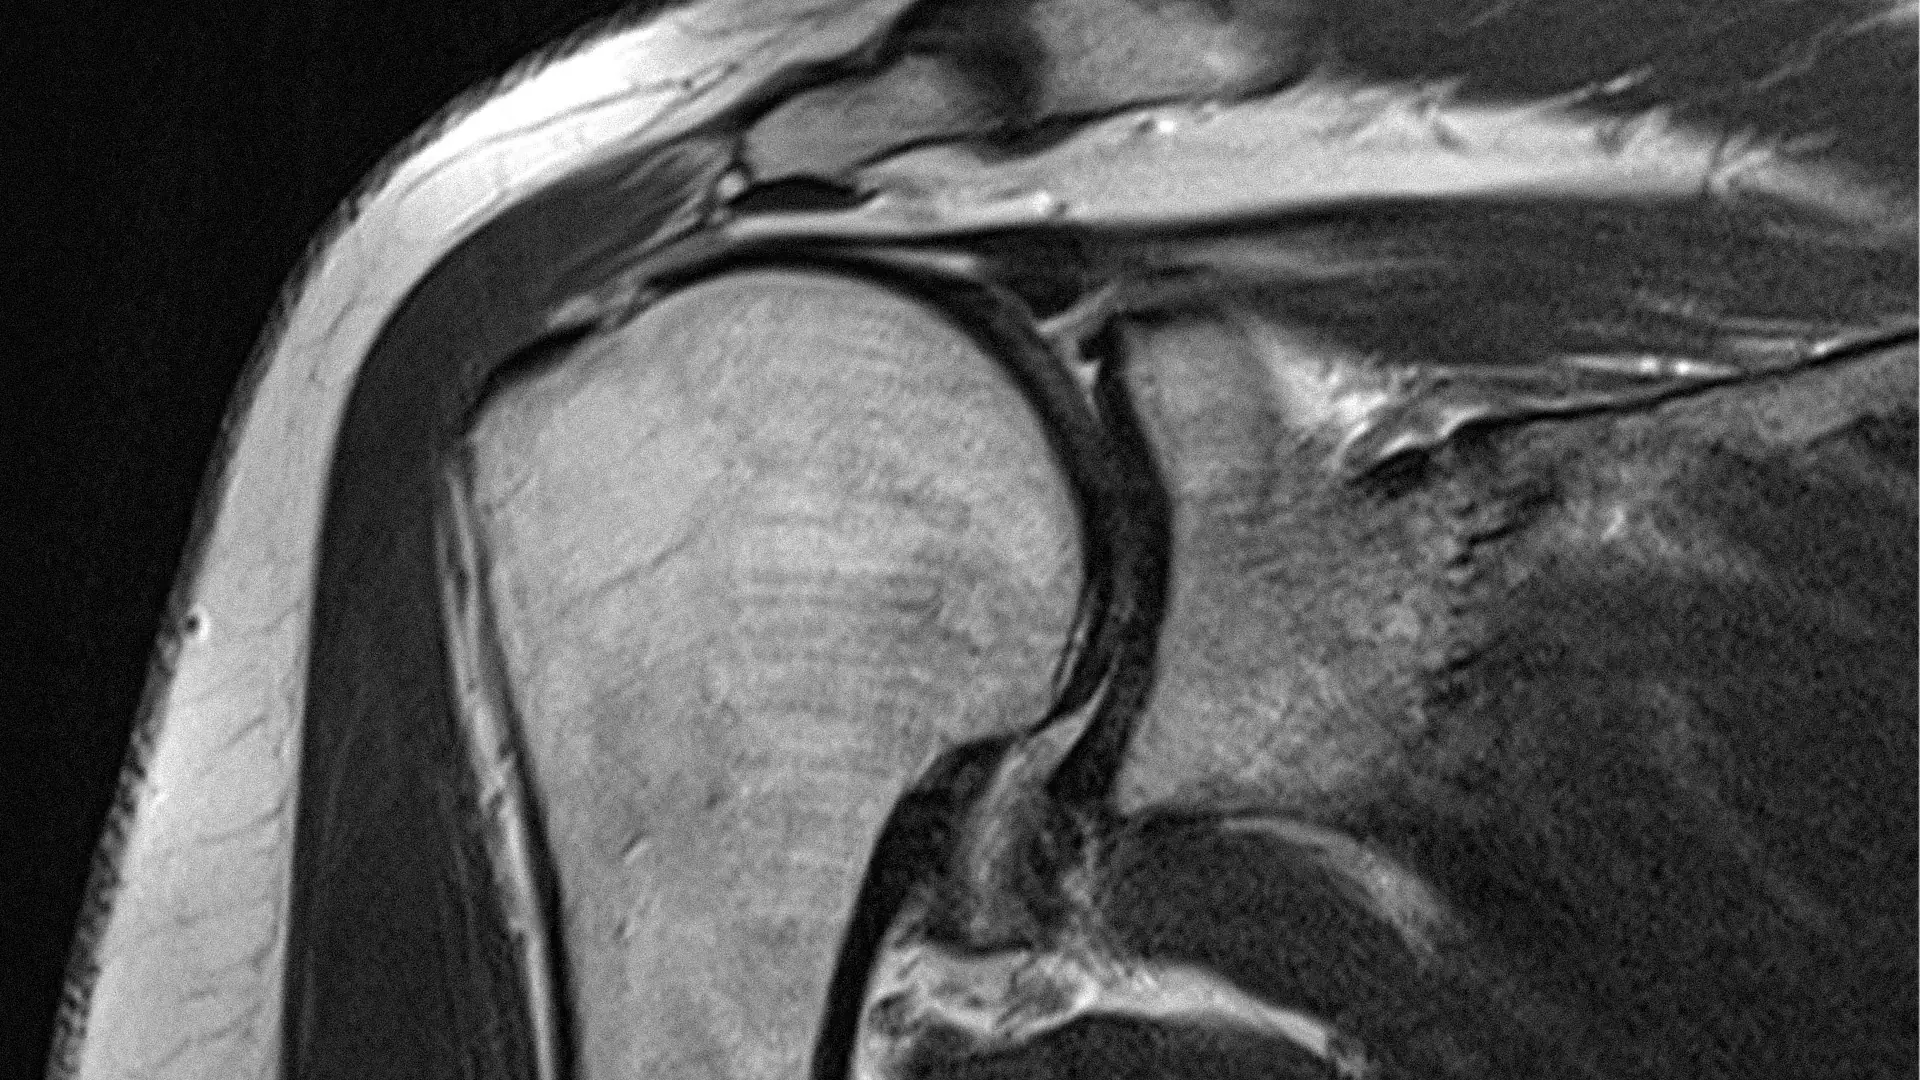
What decides whether a rotator cuff repair holds long term is the biology at the tendon-to-bone junction, a naturally poor healing environment even before injury. Blood supply is limited there even in healthy shoulders, and it gets worse with age and prior injury. Scar tissue forms instead of true tendon-bone integration, and scar tissue is mechanically weaker. Even under just normal use, it eventually gives.
This is why cortisone and rest can quiet the pain of a tear without helping the tissue rebuild.
What MSCs Are Doing at the Repair Site
MSCs change the biological conditions at the healing site in ways that go well beyond simply filling the tear:
- They differentiate into tenocyte-like cells and contribute directly to new tendon tissue
- They release anti-inflammatory signals (IL-10, TGF-beta) that shift the repair site away from chronic low-grade inflammation, which otherwise keeps re-injuring the healing tissue
- They recruit the body's own repair cells to the area and support new blood vessel growth into a naturally poor-blood-supply zone
- They support a more organized collagen structure at the tendon-bone junction than the disorganized scar tissue that tends to fail under load
None of this is exotic. It's the same set of mechanisms MSCs use in cartilage and disc tissue, applied here to a specific structural problem: a healing junction that lacks the blood supply, cellular signaling, and structural support it needs.
The Cells Matter
The outcomes above depend entirely on how many living, active cells reach the injury. This is where dosing and viability mean everything for a successful treatment.
At SOMA, every batch of mesenchymal stem cells comes from ethically sourced umbilical cord tissue and is verified at 98% viability through flow cytometry on the day of treatment. This happens in our own ISO Class 6 GMP laboratory, the only one of its kind in North America. The industry standard for cell viability, based on independent third-party testing, runs closer to 12%.
That difference is the entire mechanism behind results like the one in the study above.